Hey everyone, let’s cut to the chase. I’m the lead guy at a company that makes and ships those budget-friendly autoclave endoscopes—you know, the ones we’re all hyping as game-changers for low-resource settings. But here’s the thing: I’ve spent the last 5 years bouncing around developing countries, from small clinics in rural Kenya to mission hospitals in northern India, and I’m here to tell you that “economical” doesn’t equal “plug and play.” There’s a mountain of unspoken challenges that no marketing brochure’s gonna tell you about, and if you’re a buyer out there considering grabbing one of these, you need to hear the real deal before you sign off on anything. Economical Autoclave Endoscope

First up, the infrastructure mess. Let’s start with electricity, because that’s the big one. Most economical autoclave endoscopes are designed to plug into a standard wall outlet, right? But in a lot of these countries, the grid’s… sketchy. Like, you might get 2 hours of power a day, then a 12-hour blackout. Sure, some of the midrange models have a backup battery, but that battery’s garbage if you don’t have a way to charge it reliably. I once visited a clinic in Tanzania where they had a backup generator, but the guy who ran it skipped maintenance for 6 months—fuel line clogged, engine seized. They had a brand new economical endoscope sitting in a closet, unused, because they couldn’t count on power to autoclave the scopes between patients. And it’s not just outages. Voltage fluctuations are huge too. That cheap autoclave’s circuit board isn’t built to handle 110V one minute, 220V the next, then 110V again because a nearby factory just kicked on a motor. I’ve seen three of our units fry within a year in a Nigerian clinic because they didn’t have a basic voltage stabilizer, which costs like $50 but nobody told them they needed it. That’s a problem we didn’t factor into our original design, and it’s been a rough lesson.
Then there’s the water supply. Autoclaves, even the economical ones, need specific water—distilled or at least demineralized—because tap water has all this junk: minerals, sediment, bacteria. In a lot of developing areas, distilled water isn’t easy to get. The closest store might be 2 hours away, and even then, it’s often fake—tap water put into used plastic bottles, labeled as distilled. So clinics end up using tap water, and what happens? Scale builds up in the heating element, clogs the lines, and before you know it, the autoclave can’t reach the required temperature to kill pathogens. I talked to a nurse in Peru who used tap water for 3 months, and their economical autoclave was only hitting 121°C instead of the required 134°C—that’s a huge deal, because that means they’re not actually sterilizing the endoscopes. They were reprocessing scopes with a machine that’s not working right, and they had no idea until we did a check. The replacement heating element costs $150, but the clinic didn’t have that kind of cash, so they were stuck. Also, a lot of these places don’t have proper plumbing, so water might sit in tanks that aren’t cleaned, adding more gunk into the mix. That’s a hidden cost no one budgets for when buying an economical unit.
Next, skill gaps. Here’s the thing: an autoclave endoscope isn’t a microwave—you can’t just push a button and walk away. You need to know how to load the scopes correctly, how to set the right cycle, how to test that it’s actually working, and how to do basic maintenance. But in a lot of these settings, the staff who use them are nurses, not specialized biomedical technicians. They might have a day or two of training when they get the unit, but that’s not enough. I visited a clinic in Bangladesh where the nurse was loading the endoscopes upside down in the autoclave—so the sterilant couldn’t reach the working channels. She thought “closed end down” meant what it didn’t, basically. And when the cycle finished, she didn’t know how to check the indicators; she just assumed it was good because the light turned green. Then there’s maintenance. Simple things like cleaning the drain filter, or lubricating the door seal—stuff that takes 5 minutes, but if you don’t do it, the autoclave breaks faster. Most of these clinics don’t have a maintenance manual that’s translated into the local language, and even if they did, the staff might not be literate enough to follow it. I once had a clinic in Ghana call me in a panic because their autoclave “stopped working”—turns out the filter was clogged with lint, and it took 10 seconds to clean, but they didn’t know that was a thing. They thought they needed a whole new unit. That’s a huge, underrated challenge: you can have the best economical machine in the world, but if the people using it don’t know how to use or maintain it, it’s useless.
Then there’s supply chain for replacement parts and consumables. Let’s be real: even the most reliable economical autoclave endoscope is going to need replacement parts eventually. A seal wears out, a heating element burns, a pressure gauge needs calibrating. But in a lot of developing countries, getting those parts is a nightmare. I had a client in Uganda whose door seal broke—they needed a $20 rubber ring. The closest distributor for our parts was in Nairobi, which is 8 hours away by road, and they only had one seal in stock. It took 2 weeks to get there, and in the meantime, the clinic had to halt all endoscopic procedures because they couldn’t sterilize the scopes. That’s a huge hit to their patient care, and they had to turn away people who needed endoscopy for things like ulcers or cancer screening. Consumables too: sterilization indicator strips, distilled water pouches, channel cleaners. These are small, low-cost items, but if you can’t get them, the autoclave is useless. A lot of clinics will go for months without indicator strips because they can’t afford to order them, or the delivery is delayed. So they rely on the light or the timer, which is not accurate. That’s a safety risk we have to own, because we don’t make it easy for them to get those parts quickly and affordably.
Cost is another one, even though it’s supposed to be “economical.” Wait, hear me out. The upfront cost is low—our units are half the price of a midrange autoclave endoscope from a big brand, right? But when you add up all the hidden costs, it’s not as cheap as it seems. You need a voltage stabilizer ($50), distilled water ($10 a month for a small clinic), replacement parts ($100-$200 a year), regular maintenance checks ($150 a year). For a small clinic that makes $500 a month, that’s $50 a month just for the extras on top of the unit’s $1,000 price tag. That adds up, and a lot of clinics don’t budget for those things. They see the low upfront cost, jump on it, and then a few months later, they can’t afford to keep it running. I had a clinic in Kenya that bought our unit because it was $800 cheaper than the big brand, but they couldn’t afford the $50 stabilizer, and their unit fried after 3 months. They ended up having to buy the more expensive unit anyway, because they couldn’t afford repairs. So the “economical” tag is a trap if you don’t account for the total cost of ownership.
Also, regulatory and compliance stuff. A lot of developing countries don’t have strict medical device regulations, but some do. For example, in Brazil or South Africa, you have to get the unit certified by the local health authority, which is a big hassle. We’ve had to spend months working through certification processes in those countries, and that delays delivery, which makes it harder for clinics to get the units when they need them. Even when there’s no strict regulation, there’s still a lack of standardization in reprocessing practices. Some countries have guidelines, but they’re not enforced, so clinics don’t follow them correctly. That means even if you have a good autoclave endoscope, if the reprocessing steps are wrong, you’re still at risk of infection. We’ve had clinics that skip the pre-cleaning step for endoscopes before autoclaving—so all the blood and tissue is still on the scope, and the autoclave can’t sterilize it. That’s a compliance and education thing, not a machine thing, but it’s a huge challenge that affects how well our units work.
Wait, but let’s not make it all doom and gloom. I’ve seen these units work wonders. There’s a clinic in rural Tanzania that had no endoscopic capacity at all, and after they got our unit, they can now do ulcer screenings and remove small polyps without having to send patients 10 hours away to a big hospital. That’s life-changing. But the point is, if you’re gonna invest in one of these, you can’t just show up with a box and walk away. You have to address these challenges upfront.
So, what can we do? For our part, we’re working on redesigning the economical units to handle voltage fluctuations—building in basic surge protection, and making the circuit boards more robust. We’re also coming out with a portable backup battery that’s specifically sized for our units, so clinics don’t have to source aftermarket stuff. We’re translating all our manuals into 12 local languages, and we’re offering free 2-week on-site training for clinics that order more than one unit. We’re also setting up local parts depots in 5 more countries by next year, so replacement parts don’t take weeks to get there. And we’re working with local NGOs to help clinics budget for the hidden costs—like putting together a total cost of ownership calculator, so they know exactly what they’re signing up for, not just the upfront price.
If you’re a clinic manager, a procurement officer, or someone who’s looking to get an economical autoclave endoscope for a developing region, don’t just go for the cheapest option. Ask the hard questions: What’s the total cost of ownership? Do you have a local parts supply? What kind of training is included? How does the unit handle power and water issues? Because the last thing you want is a shiny new machine sitting in a closet because you didn’t plan for the real-world challenges.
I’ve been in this game long enough to know that the best intentions mean nothing if you don’t account for the ground realities. Our economical autoclave endoscopes are great when paired with the right support, infrastructure, and training. But ignoring these challenges is a disservice to everyone—both us as a supplier and the patients who need proper endoscopic care.
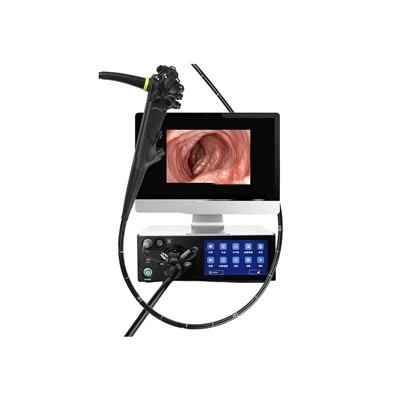
If you’re interested in learning more, or want to chat through what your specific setting needs, hit us up. We’re here to help make this work, not just sell a product.
Electronic Endoscope References:
- World Health Organization. (2021). Medical Device Safety in Low- and Middle-Income Countries: Addressing Barriers to Access and Use. WHO Press.
- Global Initiative for Gastroenterology. (2022). Reprocessing Endoscopes in Resource-Limited Settings: A Practical Guide. GIG Publications.
- United Nations Development Programme. (2020). Energy Access and Medical Infrastructure: Challenges and Solutions for Rural Clinics. UNDP Report.
- International Organization for Standardization. (2019). ISO 13485: Medical Devices—Quality Management Systems Requirements for Regulatory Purposes. ISO.
- Path. (2021). Essential Medical Devices for Low-Resource Settings: Affordability, Access, and Impact. Path International.
Zhejiang Jiacheng Medical Instrument Co., Ltd.
We’re well-known as one of the leading economical autoclave endoscope manufacturers and suppliers in China, specialized in providing high quality customized service to global clients. Please feel free to buy discount economical autoclave endoscope from our factory. Contact us for more details.
Address: Building 8, Shutai · Fuchun Innovation Park, No. 516, Majia Road, Fengchuan Subdistrict, Tonglu County, Hangzhou, Zhejiang Province, China
E-mail: Ken.huangfu@jiachengmedical.com
WebSite: https://www.jiachengmedical.com/
